

News|Articles|September 14, 2026
From Immunotherapy to Radiation: Experts Navigate Treatment and Toxicity in Cutaneous Oncology
Author(s)Shannon Heaning, Content Associate
Listen
0:00 / 0:00
Key Takeaways
- Combination ICI therapy improves response and durability versus monotherapy but demands individualized risk–benefit assessment in immunologically complex populations and proactive toxicity surveillance.
- Immune-related cutaneous toxicities may reflect any autoimmune phenotype, with melanoma and RCC carrying higher risk and remote inflammatory dermatoses capable of reactivating after ICI initiation.
The final session of the Cutaneous Oncology Workshop explored advances in systemic therapy, management of immunotherapy-related skin reactions, and the role of radiation.
Advertisement
The final educational session of the Dermatology Times Cutaneous Oncology Workshop in Tampa, Florida, brought the day's discussions full circle, moving from
During the Treatment & Management session, faculty explored advances in systemic therapy, recognition and management of
Immunotherapy Has Changed the Treatment Landscape
Amy Spizuoco, DO, opened the session by reviewing developments in cutaneous oncology treatment, including the evolution of
Combination checkpoint blockade can provide higher response rates and durable disease control compared with monotherapy in appropriate patients, but those benefits come with increased toxicity, Spizuoco explained.
The balance between efficacy and toxicity becomes particularly important in special patient populations. Patients with preexisting autoimmune disease, solid organ transplants, poor performance status, or chronic viral infections may require additional consideration when immunotherapy is being evaluated.
For clinicians, the expanding use of immune checkpoint inhibitors (
Immunotherapy Toxicity Can Involve Nearly Any Organ
Angad Chadha, MD, then focused specifically on cutaneous immunotherapy reactions, emphasizing that immune activation intended to target cancer can also produce inflammatory toxicities throughout the body.
“If you think about any organ that has an autoimmune disease that you've heard about, something that looks like that autoimmune disease can be turned on by immunotherapy,” Chadha told attendees.
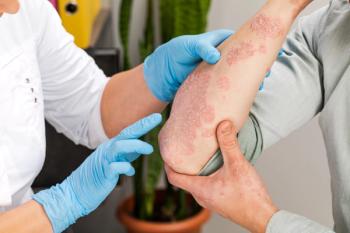
Checkpoint inhibitor toxicities can affect numerous organ systems, with potential manifestations ranging from thyroiditis and hepatitis to pneumonitis, colitis, neurologic disease, and multiple dermatologic conditions. Cutaneous manifestations include inflammatory dermatitis, bullous eruptions, pigmentary disorders, pruritus, psoriasis, and potentially life-threatening severe cutaneous adverse reactions.
Certain patients may be more susceptible. Risk factors discussed during the session included preexisting inflammatory diseases such as psoriasis, vitiligo, eczema, lichen planus, sarcoidosis, and autoimmune bullous disease. Melanoma and renal cell carcinoma have also been associated with a greater risk of cutaneous irAEs.
During the closing Q&A, Chadha noted that a remote history of inflammatory disease can remain clinically relevant. Even psoriasis that has been quiescent for years, for example, may reemerge after initiation of immunotherapy.
Treating the Skin Can Help Patients Stay on Cancer Therapy
ICI-related eczema and pruritus are among the reactions Chadha encounters most frequently.
Eczema commonly develops within the first several months of treatment, although Chadha cautioned that clinicians may see it much sooner. Presentations can resemble classic atopic dermatitis or appear as nummular, dyshidrotic, or asteatotic dermatitis.
His broader message was that clinicians should not undertreat these reactions simply because the patient is receiving cancer therapy.
For mild eczema, topical therapy may be sufficient. When it is not, Chadha discussed targeted systemic options and emphasized communication with the patient's oncology team. The goal is not only to improve the skin disease but also to help patients remain on their anticancer treatment when clinically appropriate.
“The quicker you get their condition under control, the longer and more likely they are to be able to stay on immunotherapy, which is always our goal,” Chadha said.
The workshop materials similarly note that cessation of ICI therapy is rarely required for ICI-associated eczema, although oncology coordination is necessary before initiating certain systemic treatments.
Pruritus Requires Looking Beyond the Itch
Immunotherapy-associated pruritus may occur at any point following the first treatment cycle and can even develop after treatment has been discontinued. It may appear independently or alongside an inflammatory eruption.
Chadha encouraged clinicians to consider whether persistent itch could signal another process rather than treating the symptom in isolation. Depending on the presentation, evaluation may include bullous pemphigoid antibodies, kidney and hepatic function, thyroid testing, and bile acids. A patient's history of inflammatory dermatologic disease should also be assessed.
Management varies with severity. Mild disease can often be treated while immunotherapy continues, whereas moderate or severe symptoms may require holding immunotherapy, systemic corticosteroids, dermatology consultation, or additional therapies.
Bullous Pemphigoid May Appear Long After Treatment Begins
Timing can provide another important clue when evaluating an immunotherapy-treated patient.
ICI-associated bullous pemphigoid (BP), for example, may develop months to years after immunotherapy begins or even following discontinuation. The disease can include a prolonged prodromal period of pruritus before moderate to severe blistering develops.
Chadha stressed the importance of performing the appropriate diagnostic workup when BP is suspected. This can include BP180 and BP230 antibody testing as well as biopsy for direct immunofluorescence.
Treatment then depends on severity. Mild disease may be managed with high-potency topical corticosteroids and other therapies while clinicians consider whether immunotherapy needs to be held. More extensive disease can require systemic corticosteroids and agents such as dupilumab, omalizumab, or rituximab, along with urgent dermatology involvement. Severe or life-threatening disease may require discontinuation of immunotherapy and inpatient management.
Lichenoid dermatitis, by comparison, tends to develop earlier, approximately 6 weeks to 3 months following ICI initiation, and typically presents with pruritic, polygonal, pink-violaceous papules with overlying scale.
Recognizing the Reactions That Cannot Be Treated Through
Although many cutaneous irAEs can be managed while preserving cancer treatment, Chadha drew a firm distinction when discussing severe cutaneous adverse reactions such as
SJS/TEN occurs in less than 1% of patients receiving ICIs but can be life-threatening. SJS involves less than 10% body surface area (BSA) epidermal detachment, SJS/TEN overlap involves 10% to 30%, and TEN involves more than 30%. Patients may initially develop nonspecific systemic symptoms before progressing to targetoid lesions, vesicles, bullae, epidermal necrosis, and sloughing.
“This is not something you can treat through,” Chadha said.
ICI therapy should be permanently discontinued in patients with SJS/TEN, and inpatient multidisciplinary supportive care is required. Dermatology consultation is essential, with other specialties involved according to mucosal and systemic involvement.
During the Q&A, Chadha put the risk into perspective. Pruritus is relatively common, he said, whereas severe reactions such as SJS/TEN occur in fewer than 1% of patients. Intermediate reactions including ICI-induced psoriasis, lichen planus, and BP are also considerably less common.
An SJS/TEN Mimicker Clinicians Should Recognize
Chadha also introduced attendees to progressive immunotherapy-related mucocutaneous eruption (PIRME), a rare condition that can clinically and histopathologically resemble SJS/TEN.
The distinction matters.
PIRME generally develops weeks to months after ICI initiation. Patients may first experience a relatively mild morbilliform, urticarial, or eczematous eruption that improves with topical corticosteroids, only to develop a severe mucocutaneous eruption weeks later. Findings can include bullae, full-thickness epidermal necrosis, mucosal involvement, subepidermal clefting, and a positive Nikolsky sign. Unlike classic SJS/TEN, ocular mucosa is often spared.
“If you see someone that looks like SJS/TEN, but there's no eye involvement, I want you to think about this,” Chadha said.
There are currently no standardized treatment guidelines for PIRME. However, systemic corticosteroids can produce a rapid response, with steroid tapering guided by clinical improvement.
Where Does Radiation Fit?
Amit Om, MD, closed the formal presentations by turning to another component of the skin cancer treatment arsenal: radiation therapy.
Radiation oncology is one arm of a multidisciplinary approach that also includes dermatology, Mohs or surgical oncology, and medical oncology. Advanced practice providers can play an important role in identifying potential candidates and facilitating timely referral.
Radiation does not occupy the same place across every form of skin cancer. Definitive and adjuvant radiation are established options for selected patients with BCC and cSCC.
Om encouraged attendees to think of radiation as one option within a broader treatment conversation rather than as an automatic alternative to surgery.
“When a patient comes to me with a skin cancer, before we do anything, I talk to them about all the options that we have for treatment,” he said. “At the end of the day, it's their decision.”
The Patient Matters as Much as the Tumor
Determining whether radiation is appropriate requires considering far more than the pathology report.
Older patients, those taking anticoagulants, patients with poor wound healing, and individuals with cardiopulmonary disease that makes surgery or anesthesia difficult may be reasonable candidates. Om also raised a practical issue familiar to clinicians treating patients with numerous skin cancers:
“We've done 20 Mohs on them and they're like, ‘I'm done. I don't want to do the 21st,’” he said. “Well, then we start thinking about the other options.”
Radiation is not considered the default first-line option for younger patients. Previous radiation to the same field is another important consideration, and radiation should be avoided in patients with
Anatomic location matters as well. Radiation may be attractive when surgery risks compromising function, cosmesis, or wound healing, including selected tumors involving the nose, ear, periocular region, or lip. Other locations, including skin overlying thin cartilage, hands and fingers, and previously irradiated fields, warrant additional caution.
Definitive vs Adjuvant Radiation
Om also distinguished between definitive radiation, in which radiation serves as the primary treatment, and adjuvant radiation, which is administered following surgery because residual risk remains despite tumor removal.
Definitive radiation may be considered when a patient cannot or does not want to undergo surgery, disease is unresectable, surgery could compromise function or cosmesis, or significant comorbidities affect surgical candidacy.
Adjuvant radiation becomes particularly relevant when a tumor has high-risk characteristics, including margins that cannot be corrected surgically, gross perineural invasion, poor differentiation, aggressive histology, deep or lymphovascular invasion, or large tumor size.
“Even though you think you got clear margins doing Mohs, it's like even if there's a few cells left behind, that can come back and haunt the patient later,” Om said while discussing aggressive cSCC.
But the potential oncologic benefit must be weighed against treatment burden. Om noted that a conventional course may require numerous visits to radiation oncology, creating
“It's not a small thing,” he said. “But if you need to do it, you need to do it.”
Ending the Day With Multidisciplinary Care
The workshop concluded with faculty and attendees discussing how these decisions translate into everyday practice.
The final session reinforced a theme that had emerged throughout the day: modern cutaneous oncology increasingly requires clinicians to understand not only how to identify and remove a skin cancer, but how to manage patients across an expanding continuum of care.
For APPs in particular, that may mean recognizing an immunotherapy-associated eruption before it becomes severe, helping patients remain on lifesaving cancer treatment when an adverse event can be safely managed, identifying when a tumor warrants discussion of adjuvant radiation, or coordinating referral among dermatology, surgery, medical oncology, and radiation oncology.
As newer systemic treatments continue to improve outcomes, the role of dermatology is expanding alongside them. For clinicians caring for patients with skin cancer, successful treatment increasingly depends not on a single modality, but on knowing when to treat, when to escalate, and when to bring another member of the multidisciplinary team into the conversation.
References
- National Comprehensive Cancer Network. Management of immune checkpoint inhibitor-related toxicities. Version 1.2026.
https://www.nccn.org/guidelines/guidelines-detail?category=3&id=1548 - Apalla Z, Nikolaou V, Fattore D, et al. European recommendations for management of immune checkpoint inhibitors-derived dermatologic adverse events. Dermatol Pract Concept. 2021;11(1):e2021155.
https://pubmed.ncbi.nlm.nih.gov/34910332/ - Likhacheva A, Awan M, Barker CA, et al. Definitive and postoperative radiation therapy for basal and squamous cell cancers of the skin: Executive summary of an American Society for Radiation Oncology clinical practice guideline. Pract Radiat Oncol. 2020;10(1):8-20.
https://pubmed.ncbi.nlm.nih.gov/31831330/
Advertisement
Related Content
Advertisement

Advertisement
Advertisement
Trending on Dermatology Times
1
How Emerging Androgenetic Alopecia Therapies Target DHT at the Scalp Level
2
Tildrakizumab Partially Reverses Epigenetic Aging in Psoriasis, Pilot Study Shows
3
Merz Expands BELOTERO Portfolio With Two New FDA-Approved Hyaluronic Acid Fillers
4
FDA Grants Priority Review to Zasocitinib for Moderate-to-Severe Plaque Psoriasis
5