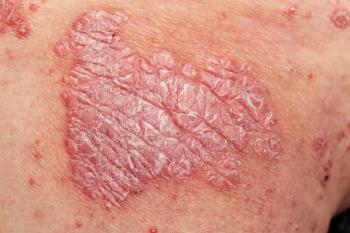
ORKA-001 achieved PASI 100 in 61% of high-dose patients at week 16 in the phase 2b EVERLAST-B trial of moderate-to-severe psoriasis.
Experts outline how to recognize undertreated psoriasis, assess incomplete response, and make individualized decisions when escalating therapy.
The treatment landscape for psoriasis has changed dramatically over the past decade. We are now practicing in an era with the most diverse and effective psoriasis treatments we have ever had—biologics, small molecules, and now oral peptides. Despite these options, there are still patients on therapy who remain undertreated. The challenge is no longer a lack of treatment options, but rather recognizing when disease control is inadequate, identifying the factors contributing to an incomplete response, and selecting the next best treatment option.
As the efficacy of psoriasis treatments evolves,
Perhaps one of the easiest mistakes to make in psoriasis management is continuing a treatment simply because it is working well enough. A patient returns for follow-up, reports that they are “doing pretty well,” has no significant adverse effects, and needs refills. This is particularly relevant for patients who have been on the same biologic for many years. The follow-up question should not only be “Is this medication still working?” but also “Is this still the best level of disease control we can reasonably achieve for this patient?”
If their psoriasis is substantially improved from baseline, it can be tempting to renew the same medication and revisit the issue at the next appointment. Over time, however, this can result in patients remaining on therapies that provide acceptable—but not optimal—disease control. Continuing a treatment should be an active decision rather than the default.
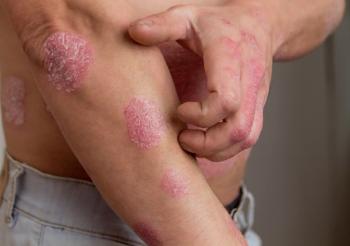
Recognizing undertreatment starts with looking beyond body surface area. BSA assessment during psoriasis visits is useful, practical, and often necessary for documentation. However, it does not always capture the full burden of psoriatic skin disease. A patient with limited BSA may have psoriasis affecting high-impact areas, such as the scalp, hands, feet, nails, face, and genital skin. Involvement of these particular sites is associated with worse quality of life and greater limitations in social and daily activities, even after adjusting for BSA.2
Equally important, improvement in BSA over time does not always mean adequate disease control. Consider a patient who presents with severe psoriasis involving 30% BSA before starting advanced systemic therapy. At follow-up, their BSA has improved to 15%. This patient may understandably be thrilled with the significant reduction in their psoriasis. However, they may not realize that substantially greater improvement may still be achievable with the highly effective treatments available today. As clinicians, we can also allow a dramatic improvement from baseline to serve as the end point, rather than asking whether the patient has actually reached an acceptable treatment goal. Treatment goals vary substantially between patients, reinforcing the importance of asking what matters most to the individual rather than assuming that improvement alone represents success.1
Beyond the skin, recognizing undertreatment requires assessment for
Our expectations for psoriasis treatment have also evolved.
The goal is not to switch therapy for every patient who has a residual plaque. Instead, it is to recognize when clinically meaningful disease remains and make an active decision about whether the current level of control is acceptable. At follow-up, asking where psoriasis is still present, which symptoms remain bothersome, whether joint symptoms have developed, and how the disease continues to affect the patient’s daily life can help distinguish a patient who is truly well controlled from one who is simply much better than before.
A common mistake when escalating therapy is assuming that an incomplete response automatically represents treatment failure. Once we recognize that a patient is not at an acceptable treatment goal, the next step is to determine why. Before changing therapy, it is important to confirm that the patient has been adherent to the medication, has received it at the appropriate dose and for an adequate duration, and has not had significant interruptions in treatment. Real-world data from commercially insured US patients with moderate to severe psoriasis demonstrate that adherence and persistence to biologic therapy vary considerably.
It is also important to differentiate an inadequate initial response from a loss of response over time. A patient who never achieves meaningful clearance despite an adequate trial presents a different clinical situation than a patient who initially responds very well and later begins to experience recurrence. This distinction helps clarify whether the current therapy never adequately controlled the disease or whether it was effective but lost durability over time.
The extent and location of residual disease are also important. A patient who remains otherwise well controlled but develops a few persistent scalp plaques may be managed with topical treatment directed at that specific site rather than by stopping an otherwise successful therapy. In this situation, the systemic therapy may still be providing excellent overall disease control. In contrast, a patient who begins developing plaques across multiple body areas after previously achieving near-complete clearance has a broader loss of disease control and may require a change in systemic therapy.
Before concluding that the current therapy has failed, it is also worth confirming that residual or new skin findings are actually psoriasis. A persistent eruption may instead represent seborrheic dermatitis, tinea, contact dermatitis, eczema, or another diagnosis, and escalating systemic psoriasis therapy will not address the wrong condition. Changes in the patient’s overall health, including new comorbidities or joint symptoms, may also affect both treatment goals and the next treatment decision.
Ultimately, the goal is to understand what has failed before deciding what should come next. Is the current therapy truly providing inadequate efficacy? Did the patient never achieve an adequate response, or has a previously successful response been lost? Are treatment interruptions contributing? Is the remaining disease localized or widespread? Answering these questions helps avoid reflexively switching therapies and allows the next treatment decision to be more deliberate and individualized. A practical approach to this reassessment is summarized in the Table.
Table. A Practical Framework Before Escalating Psoriasis Therapy
Clinical Consideration
Key Question
Treatment Implication
Treatment goal
Is the patient truly at goal?
Improvement from baseline does not necessarily mean adequate disease control.
Adequate trial
Has treatment been given at the appropriate dose and for an adequate duration?
An incomplete trial should not be mistaken for treatment failure.
Treatment access
Have there been missed doses, insurance delays, or interruptions in therapy?
Gaps in treatment can mimic loss of efficacy.
Disease burden
Is residual psoriasis affecting a high-impact area or meaningful quality-of-life domain?
Limited BSA can still represent clinically significant disease.
Pattern of response
Was the initial response inadequate, or was a good response later lost?
Primary nonresponse and secondary loss of response provide different information when considering the next step.
Extent of recurrence
Is the remaining disease localized or widespread?
Localized disease may be managed adjunctively, whereas widespread recurrence suggests broader loss of systemic control.
Confirm the diagnosis
Is the residual or new eruption actually psoriasis?
Escalating psoriasis therapy will not treat an alternative diagnosis.
Patient factors
Have joint symptoms, comorbidities, treatment priorities, or other circumstances changed?
Changes in the patient may alter both treatment goals and the most appropriate next therapy.
Once the decision has been made to change systemic therapy, another common mistake is choosing the next treatment as though there is a predetermined sequence of medications. With the number of highly effective therapies now available for psoriasis, there is rarely a single “next” drug that is appropriate for every patient. Efficacy is important, but treatment selection should also incorporate the reason for the change, the patient’s prior treatment history, comorbidities, disease characteristics, safety considerations, treatment preferences, and access.7
The patient’s previous response can be particularly helpful. For example, consider a patient who achieved near-complete clearance with
Patient preference should also play a meaningful role. One patient may prioritize infrequent injections and prefer risankizumab, with maintenance dosing every 12 weeks.9 Another may strongly prefer to avoid injections altogether. Oral treatment options now extend beyond traditional systemic agents and include targeted therapies such as
Ultimately, selecting the next treatment should start with asking 2 questions: Why was the current treatment not enough, and what do we want the next treatment to do differently? The goal is not simply to replace one medication with another but to use what we learned from the patient’s previous treatment experience to make a more intentional and individualized choice.
Escalating therapy in psoriasis is not simply about moving from one medication to the next. It requires recognizing when a patient is not truly at their treatment goal, understanding why the current treatment is falling short, and using that information to make a more thoughtful next choice. With the effectiveness of current therapies, improvement alone should not automatically be considered success.
At the same time, the goal is not to switch treatments simply because newer options are available. Continuing therapy should be an active decision rather than the default. At each follow-up, it is worth asking whether the patient’s disease is adequately controlled, whether residual psoriasis is still affecting their quality of life, and whether the current treatment continues to meet their goals.
Perhaps the most useful question is also one of the simplest: If we were choosing a treatment for this patient today, would we still choose the one they are currently taking? If the answer is no, it may be time to reconsider the treatment plan.
Sarah Tonelli, MD, is a board-certified dermatologist practicing at Brinton Lake Dermatology in Glen Mills, Pennsylvania.
References
about 24 hours ago
A Clear Road Map for Severe Alopecia Areata7 days ago
Skin Longevity Needs Evidence, Not Hypeabout 1 month ago
Sun Protection in Beauty Routines: Is SPF Makeup Enough?about 2 months ago
Mind the Gap: Will Digital Replace Clinical?