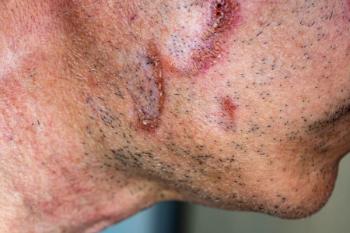
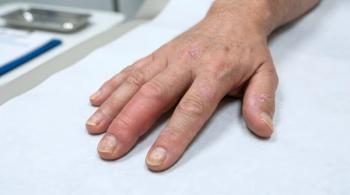
At a Dermatology Times Case-Based Roundtable event, Carolyn Goh, MD, led clinicians through a discussion of severity scoring, patient-reported outcomes, CYP2C9 testing, and long-term monitoring across 3 alopecia areata cases.
Gaurav Singh, MD, explores how gene expression profiling may improve melanoma risk stratification, surveillance, and individualized care.
Although American Joint Committee on Cancer (
In an expert discussion with Dermatology Times, Gaurav Singh, MD, a Mohs surgeon at City of Hope Cancer Center in Chicago, examined the clinical utility of GEP testing in cutaneous melanoma, including its potential role in sentinel lymph node biopsy (SLNB) decisions, surveillance strategies, and integration with emerging biomarkers.
Singh emphasized that although AJCC staging incorporates established prognostic factors such as Breslow thickness, ulceration, and nodal status, it does not account for every characteristic that may influence melanoma outcomes.
Tumor location, mitotic activity, and immunosuppression may contribute to differences in disease behavior, potentially leaving some patients at greater risk than their initial staging suggests.
Singh explained that patients with stage I melanoma may experience recurrence or metastasis despite receiving standard-of-care treatment, whereas some patients with more advanced disease achieve favorable outcomes following surgery and immunotherapy.
He described GEP testing as an additional source of prognostic information that may help identify patients whose tumors demonstrate more aggressive biological characteristics than traditional staging alone would suggest.
Singh highlighted
For patients with stage I disease, a high-risk GEP result may prompt additional consideration of
In stage II melanoma, Singh described using high-risk results, including
He also discussed emerging evidence supporting the prognostic utility of 31-GEP testing, citing analyses of Surveillance, Epidemiology, and End Results (
However, the clinical utility of GEP testing remains an evolving area of investigation, and prognostic findings should not be interpreted as establishing that testing itself improves survival or replaces guideline-based management.
Despite the potential advantages of molecular testing, Singh cautioned against interpreting GEP results independently of the patient's overall clinical circumstances.
He emphasized that decisions regarding additional imaging, surgery, or surveillance should incorporate functional status, comorbidities, and patient preferences alongside estimated risk.
Singh also noted that GEP testing may offer less clinical utility in certain patients with established stage III disease and confirmed lymph node involvement, depending on the specific management question.
Importantly, he explained that a low-risk GEP result may provide reassurance even when it does not directly alter treatment recommendations. Conversely, high-risk results can help clinicians identify patients who may warrant closer observation without suggesting that disease progression is inevitable.
Looking ahead, Singh discussed the potential complementary roles of GEP testing and circulating tumor DNA (ctDNA) in melanoma surveillance.
Whereas GEP provides information about a tumor's underlying prognostic characteristics, ctDNA testing may offer a means of monitoring for molecular evidence of disease over time.
In his practice, Singh described considering serial ctDNA testing for patients with high-risk GEP results, using changes in circulating tumor DNA levels to help inform subsequent imaging decisions.
Although ctDNA testing continues to be investigated in melanoma, Singh suggested that integrating molecular prognostic assessments with longitudinal biomarker monitoring could contribute to more individualized surveillance strategies.
Ultimately, Singh emphasized that the value of GEP testing lies in its ability to supplement, rather than replace, established clinical assessments. As evidence continues to develop, the appropriate integration of molecular tools into melanoma care will depend on balancing prognostic information with clinical utility, guideline recommendations, and individual patient needs.
References