A retrospective claims analysis of 2897 matched pairs found hazard ratios of 0.48 to 0.67 for new atopic disease with dupilumab vs systemic corticosteroids in children.
Mark Lebwohl, MD, describes his approach on when to start systemic therapy, access considerations, and dupilumab safety and growth data in atopic dermatitis.
Mark Lebwohl, MD, dermatologist, Dean for Clinical Therapeutics at the Icahn School of Medicine at Mount Sinai, and Chairman Emeritus of the Department of Dermatology at Mount Sinai, discussed when to move patients with atopic dermatitis to systemic therapy. He also reviewed how age and insurance access shape agent selection, along with dupilumab (Dupixent; Sanofi and Regeneron) safety and growth data in pediatric patients.
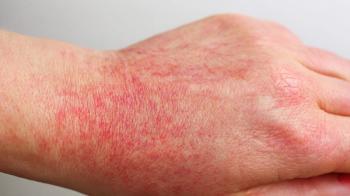
Lebwohl said patients become candidates for systemic therapy when a topical therapy is not enough. He described involvement of more than 10% of body surface area as a clear threshold, noting 10 palms of the hand equal 10%. Patients whose disease flares repeatedly and who spend much of the year applying topicals also fit.
Patients with limited disease who do not respond well enough to topical therapy are candidates as well. Some patients prefer to defer systemic therapy no matter what, and Lebwohl said topicals are used as best they can be in those cases.
“It is usually fairly obvious,” Lebwohl said.
Nemolizumab (Nemluvio; Galderma) provides rapid itch relief, according to Lebwohl, and is often used in patients whose main problem is itching. Insurance access is a major factor in selection, he said, and age at approval carries equal weight.
“We can’t get many of the drugs between the ages of 2 and 12 because they’re simply not approved,” Lebwohl said.
According to Lebwohl, dupilumab is the agent most prescribed in this age group. Copays for some drugs can be exorbitant for Medicare patients, but Lebwohl said coverage for dupilumab and nemolizumab is usually fairly easy to obtain. He noted those 2 drugs are overwhelmingly prescribed in this population.
Lebwohl said dupilumab safety data have held up over more than 10 years of use. The main finding in clinical trials was a conjunctivitis rate of approximately 10%, or roughly one in 10 patients. Increases in infections and other anticipated side effects generally do not occur.
“Fortunately, we have a lot of safety data on dupilumab,” Lebwohl said.
Lebwohl does not usually discuss cutaneous lymphoma with parents or patients. He believes the data to date suggest reported cases reflect diagnostic error, because cutaneous lymphoma can look like atopic dermatitis. Patients receive dupilumab presuming atopic dermatitis, and the lymphoma is correctly diagnosed afterward.
Before the recent data on prevention of the atopic march, data already existed on bone and growth. Lebwohl said patients with significant disease treated with topical therapy alone fail to grow, though he is unsure whether the disease, steroid absorption, or systemic steroids explain it.
“In patients treated with dupilumab, growth is greater than those treated with topical corticosteroids,” Lebwohl said.
Better disease management may explain the difference, he said. Avoiding corticosteroids may also contribute, as they are known to cause premature closure of the epiphyseal plates, resulting in shorter stature.