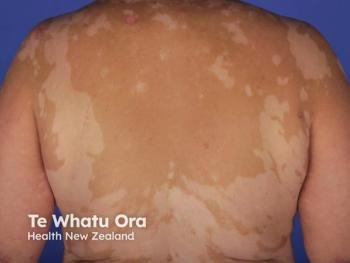
Dermatology clinicians at a Case-Based Roundtable in Austin, Texas, discussed real-world strategies for sequencing topical therapy, phototherapy, and ruxolitinib cream across pediatric and adult vitiligo cases.
Clinicians at a Dermatology Times Case-Based Roundtable, moderated by Chesahna Kindred, MD, debated when to escalate to oral JAK inhibitors for alopecia areata and how to counsel patients on timing, monitoring, and safety.
Chesahna Kindred, MD, a dermatologist and founder of Kindred Hair & Skin Center, recently led a
Attendees first split on topical therapy. Some go straight to intralesional corticosteroid injections for adults with small patches, while one reported success with compounded topical tofacitinib above 50% involvement. In the first poll, 5 of 11 respondents (45.5%) named SALT score as the top trigger for systemic therapy, and 4 (36.4%) chose psychosocial impact.
Case 1 featured a 33-year-old man with 45% scalp hair loss, a wedding in 6 months, and 4 months of topical corticosteroid use with minimal improvement. Some attendees would start injections and reassess in 3 to 4 weeks. Others favored a JAK inhibitor immediately, and 8 of 11 respondents (72.7%) called speed of response extremely influential.
Kindred reviewed efficacy data for deuruxolitinib (Leqselvi; Sun Pharma), ritlecitinib (Litfulo; Pfizer), and baricitinib (Olumiant; Eli Lilly). Counseling this patient on deuruxolitinib, “You have a 30% chance of having at least 80% scalp coverage by the day of your wedding,” Kindred said. Attendees noted continued improvement over time and dose dependence with baricitinib.
On expectations, Kindred gives every patient the same timeline: “I tell all of my patients a year,” she said. One attendee favored combining oral minoxidil, injections, and a JAK inhibitor: “I [say] you’re not married to your medication.”
Case 2 described a 29-year-old woman whose scalp hair loss rose from 21% to 36% in 3 months, with anxiety and social avoidance despite 3 months of rosemary oil and a topical corticosteroid. Attendees classified her disease as severe. Kindred said the anxiety alone would raise her severity grade.
Attendees saw similar distress in men and women, linking it to age at onset. “If you’re 15 and you’re a guy, that’s really hard,” an attendee said. In the third poll, efficacy led JAK inhibitor selection factors with 9 of 27 selections (33.3%), followed by safety (8; 29.6%) and insurance access (6; 22.2%).
Kindred reviewed patient-reported outcomes. In THRIVE-AA (
Asked what success means beyond SALT score, one attendee said, “I hate to say it this way, but hair loss is never going to kill you.” The attendee named quality of life as the priority. Attendees waited 6 months to 2 years before calling a nonresponse, and 6 of 10 poll respondents (60%) would switch to another JAK inhibitor.
Case 3 involved a 42-year-old man with 85% scalp hair loss and new eyebrow and beard involvement after 6 months of a high-potency topical corticosteroid and minoxidil. Attendees said facial involvement raises psychosocial impact and complicates injections. Kindred added the beard carries particular importance in some cultures.
Attendees described baseline labs resembling an isotretinoin panel plus TB and hepatitis screening. Kindred checks labs at baseline and at 1 to 3 months, then aligns annual monitoring with the primary care physician. She described CYP2C9 testing as FDA-mandated for deuruxolitinib, and 4 of 10 poll respondents (40%) do not order it.
On clotting risk, Kindred said the VTE case cited from each of the ritlecitinib and baricitinib datasets involved a patient with factor V Leiden. The deck showed no deep vein thrombosis, pulmonary embolism, myocardial infarction, or stroke in either THRIVE-AA trial through 24 weeks.
“I am not convinced of the clots. I haven’t seen the data yet. So please practice based on your comfort,” Kindred said.
An attendee asked whether patients stay on therapy indefinitely. “That’s what we’re finding,” Kindred said, adding about 50% keep their hair after stopping and recapture is around 80%.
In the final poll, 6 of 13 selections (46.2%) reported existing comfort with JAK inhibitors, and 4 (30.8%) chose monitoring and safety best practices. Closing comments turned to the staff time and prior authorization burden of prescribing them.
References